Your Cart is Empty
Shipping is free on orders over €60!
Shipping is free on orders over €60!

Creatine is a nitrogen-containing organic compound of a guanidine-like nature that occurs naturally in vertebrates and plays a key role in cellular energy metabolism, particularly in tissues with high and fluctuating energy demands such as skeletal muscle and the brain (Wyss and Kaddurah-Daouk, 2000; Wallimann et al., 2011). It was discovered in 1832 by the French chemist Michel Eugène Chevreul, who isolated it from an aqueous extract of skeletal muscle and named it after the Greek word kreas (meat). A few years later, Justus von Liebig confirmed creatine as a common constituent of vertebrate muscle and chemically identified it as methylguanidinoacetic acid (Wyss and Kaddurah-Daouk, 2000; Bredahl et al., 2021). The human body obtains creatine in two ways: through endogenous synthesis and through the diet. In people consuming a mixed diet, approximately half of the daily requirement is covered by endogenous synthesis and the other half by dietary intake (Brosnan and Brosnan, 2007). Biosynthesis takes place in a two-step enzymatic process from three amino acids: arginine, glycine, and methionine. In the first step, the enzyme L-arginine:glycine amidinotransferase (AGAT) catalyzes the transfer of an amidino group from arginine to glycine, forming guanidinoacetic acid. This step is rate-limiting and regulatory for the entire metabolic pathway. In the second step, the enzyme guanidinoacetate N-methyltransferase (GAMT) methylates guanidinoacetic acid using S-adenosylmethionine as the methyl-group donor, thereby producing creatine (Wyss and Kaddurah-Daouk, 2000). This synthesis takes place mainly in the liver, kidneys, and pancreas, from where creatine is distributed through the bloodstream to target tissues (Persky and Brazeau, 2001; Bredahl et al., 2021). Baseline creatine stores are not the same in all individuals. Lower muscle concentrations are more commonly observed in vegetarians and vegans, who do not obtain creatine from meat and fish, and it is precisely in these individuals that the absolute increase following supplementation is usually greater (Burke et al., 2003; Kaviani et al., 2020). However, this does not mean that people consuming a mixed diet do not respond to creatine. The difference mainly concerns the magnitude of the increase in stores that can be achieved, rather than the fundamental mechanism of action. Direct measurements have confirmed that vegetarians at rest have approximately 20 to 30% lower muscle concentrations of creatine and phosphocreatine than omnivores (Kreider et al., 2017; Kaviani et al., 2020), and women also have lower endogenous stores compared with men (Smith-Ryan et al., 2021). Variability in response is also influenced by muscle mass, the proportion of fast-twitch muscle fibers, training status, and probably the activity of the SLC6A8 transporter (Wyss and Kaddurah-Daouk, 2000; Syrotuik and Bell, 2004; Kreider et al., 2017). The main natural dietary sources are meat and fish. To illustrate, a dose of five grams of creatine corresponds to the creatine content of approximately 1.1 kg of raw beef, since beef contains around 4.5 g of creatine per kilogram, whereas certain fish species, such as herring, may contain up to 6.5 to 10 g of creatine per kilogram of raw fish (Brosnan and Brosnan, 2007; Kreider et al., 2017). The body of an adult weighing approximately 70 kg contains a total creatine pool of around 120 to 140 g, with roughly 95% located in skeletal muscle and the remainder predominantly in the brain, heart, and other tissues. Daily turnover is approximately 1 to 2 g, with creatine and phosphocreatine spontaneously and nonenzymatically converted into creatinine, which is excreted in the urine. This loss must continuously be replaced through diet or endogenous synthesis (Wyss and Kaddurah-Daouk, 2000; Kreider et al., 2017). Creatine entered broader public awareness as a sports supplement in the early 1990s, particularly following the pioneering work of Harris and colleagues. They showed that oral supplementation in the form of creatine monohydrate significantly increases total creatine content in skeletal muscle, with increases of up to approximately 50% in individuals with the lowest baseline levels, and that part of the ingested creatine is stored as phosphocreatine (Harris et al., 1992). Commercial popularity followed the 1992 Summer Olympic Games in Barcelona (Bredahl et al., 2021). Since then, creatine monohydrate has become the most extensively studied and most widely used ergogenic dietary supplement, and the International Society of Sports Nutrition position stand describes it as the most effective nutritional supplement currently available to athletes for increasing high-intensity exercise capacity and lean body mass during training (Buford et al., 2007; Kreider et al., 2017). In recent years, interest in its use outside sport has also increased, for example in relation to cognitive function, recovery, or the health of aging populations. However, the strongest evidence remains in the areas of muscle metabolism and physical performance (Avgerinos et al., 2018; Kreider and Stout, 2021; Roschel et al., 2021). Current literature therefore no longer classifies creatine exclusively as a sports supplement. It is being investigated as nutritional support during aging, sarcopenia, recovery, long-term immobilization, and situations involving increased energy demands in the brain (Kreider and Stout, 2021; Roschel et al., 2021). The indispensable physiological role of creatine, particularly in the central nervous system, is demonstrated by congenital disorders of creatine metabolism collectively referred to as cerebral creatine deficiency syndromes. Two synthesis disorders are distinguished, namely deficiency of the AGAT enzyme and deficiency of the GAMT enzyme, as well as a transport disorder resulting from mutations in the SLC6A8 gene. These conditions lead to an almost complete absence of creatine in the brain, measurable by magnetic resonance spectroscopy, and manifest as delayed psychomotor development, intellectual disability, speech disorders, epilepsy, and autistic features. In synthesis disorders, administration of high doses of creatine can partially restore brain creatine stores, whereas treatment of the transporter disorder is only of limited effectiveness because the transporter itself is absent at the blood-brain barrier (Braissant and Henry, 2008; Kreider and Stout, 2021).
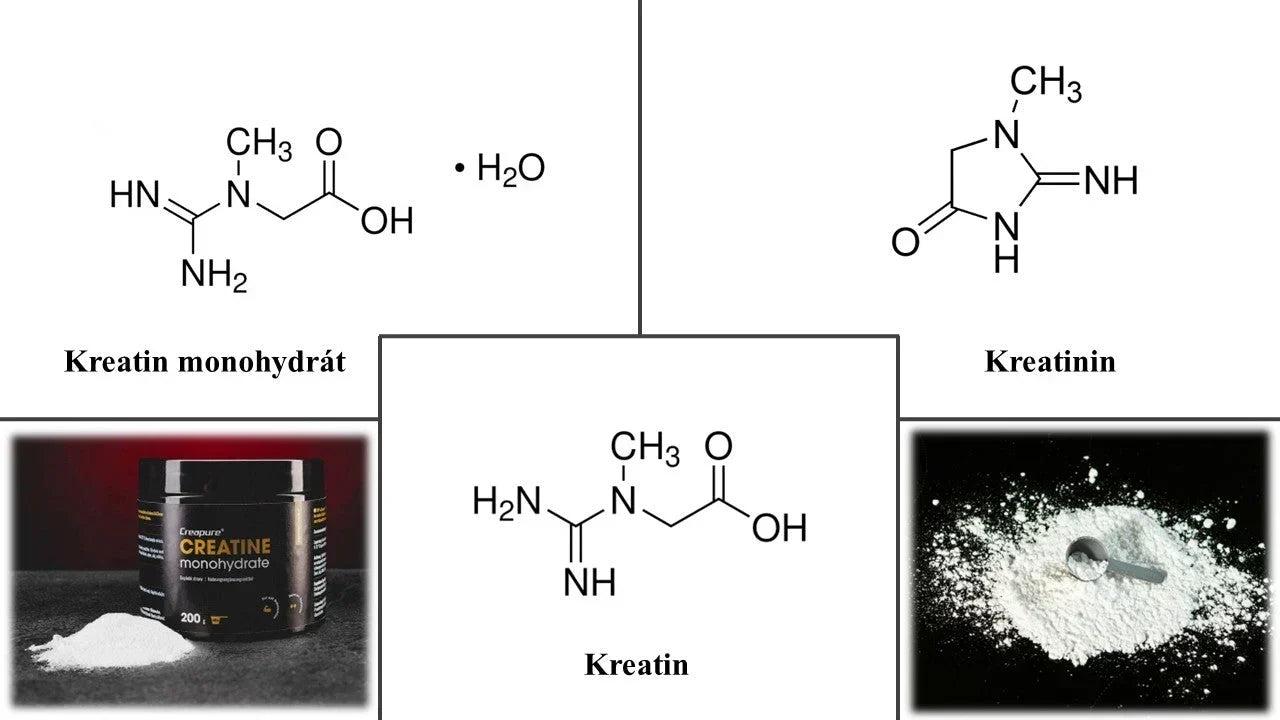
Chemically, creatine is (α-methylguanidino)acetic acid, systematically N-(aminoiminomethyl)-N-methylglycine, with the empirical formula C4H9N3O2 and a molar mass of 131.13 g/mol (Fig. 1). In dietary supplements, it most commonly occurs in the form of the monohydrate, in which one molecule of crystal water is bound to the creatine molecule. The molecular formula of the monohydrate is therefore C4H9N3O2·H2O, with a molar mass of approximately 149.15 g/mol (Fig. 1). Creatine monohydrate therefore contains approximately 87.9% pure creatine by weight, with the remainder consisting of bound water. It is a white, odorless crystalline powder that forms monoclinic crystals (Dash et al., 2002; Bonilla et al., 2021; Kreider et al., 2022). The crystal structure and physicochemical properties of creatine monohydrate have been extensively characterized using X-ray diffraction and thermal analysis. It is important to distinguish between creatine and creatinine. Creatinine is the cyclic anhydride of creatine, formed through spontaneous, nonenzymatic intramolecular cyclization with the loss of a water molecule, and represents the final degradation product excreted by the kidneys. This conversion is accelerated by lower pH values and higher temperatures (Dash et al., 2002; Jäger et al., 2011; Bonilla et al., 2021). In the solid state, creatine monohydrate is highly stable and shows no signs of degradation even after more than three years of storage at room temperature, with creatinine formation remaining below the limit of quantification (Jäger et al., 2011; Kreider et al., 2022). In aqueous solution, however, it is not stable and gradually converts into creatinine, which is why it is recommended that a drink be prepared only shortly before consumption. In practical terms, it is important to distinguish between the stability of the dry raw material and the stability of the prepared beverage (Ganguly et al., 2003; Jäger et al., 2011; Kreider et al., 2022). Experimental studies confirm the high stability of dry crystalline creatine and its gradual degradation in solution, which can be slowed by refrigeration. The conversion of creatine to creatinine follows first-order kinetics, the rate of which increases with rising temperature and, within the typical pH range of beverages, also with decreasing pH below the neutral range. The process therefore occurs more slowly under neutral or slightly alkaline conditions, whereas mildly acidic pH, heat, and prolonged storage of the solution accelerate the conversion. Dissolving creatine in juice or a warm beverage is therefore not a problem in itself, provided that the mixture is consumed shortly after preparation. In contrast, long-term storage, especially for several days, of a pre-prepared acidic solution is unsuitable (Ganguly et al., 2003; Jäger et al., 2011; Antonio et al., 2021; Kreider et al., 2022). At neutral pH, creatine is relatively stable during the first few hours, whereas degradation increases substantially when stored for several days in a more acidic environment. The phosphorylated form of creatine, phosphocreatine or creatine phosphate, is a high-energy compound that serves as a rapidly available reserve of phosphate groups for the resynthesis of adenosine triphosphate (Wallimann et al., 2011; Bonilla et al., 2021). The solubility of creatine monohydrate in water is limited and is approximately 13 g/l at 25 °C, increasing with temperature. A standard dose of 5 g therefore does not dissolve completely in 200 to 300 ml of liquid. So-called micronization, meaning a reduction in the particle size of the powder, increases the dissolution rate and improves dispersibility and wettability in liquid without altering the actual equilibrium or thermodynamic solubility of the molecule (Albagachiev et al., 2026). A stated solubility of 13 g/l means that, theoretically, approximately 385 ml of water would be required to completely dissolve 5 g at 25 °C. Compared with other chemical forms of creatine, monohydrate remains the form with the best balance of cost, effectiveness, and scientific evidence (Jäger et al., 2011; Antonio et al., 2021; Kreider et al., 2022). Greater solubility of an alternative salt or a smaller particle size is not automatically evidence of greater bioavailability. The solubility of the powder in the glass has no significant effect in itself on the uptake of creatine into tissues, provided that the entire dose is subsequently consumed (Antonio et al., 2021; Kreider et al., 2022). Comparative studies and available pharmacokinetic data generally do not show that alternative forms result in higher muscle creatine stores than creatine monohydrate. Creatine monohydrate is industrially produced by chemical synthesis from sarcosine and cyanamide. This reaction can produce undesirable by-products, particularly dicyandiamide, dihydrotriazine, and creatinine, which is why raw-material quality is checked using liquid chromatography (Benzi, 2000; Jäger et al., 2011; Moret et al., 2011; Kreider et al., 2022). Creatine monohydrate is almost completely absorbed after oral administration, and pharmacokinetic studies have shown that its clearance decreases following repeated dosing as muscle stores become increasingly saturated (Persky et al., 2003; Kreider et al., 2022). The limiting step for the long-term increase in muscle stores is therefore more likely cellular transport and attainment of intramuscular saturation than complete dissolution of the powder in the glass (Antonio et al., 2021; Kreider et al., 2022). A repeated-dose study did indeed observe a decrease in clearance, which the authors attributed to saturation of creatine stores in skeletal muscle.

Figure 1. Chemical structure of creatine (N-methylguanidinoacetic acid) and its monohydrate, in which one water molecule is bound to the molecule.
The most important biological function of creatine lies in the phosphagen energy system, known as the ATP-PCr system. During muscle contraction, adenosine triphosphate is hydrolyzed to adenosine diphosphate with the release of energy. Since cellular adenosine triphosphate stores are limited and are sufficient for only a few seconds of maximal performance, rapid resynthesis is necessary. This is provided by phosphocreatine through a reversible reaction catalyzed by the enzyme creatine kinase, in which phosphocreatine transfers its high-energy phosphate group to a molecule of adenosine diphosphate, producing adenosine triphosphate and free creatine. This system provides the most rapidly available source of energy and supplies approximately the first six to ten seconds of intense performance. It is therefore crucial for short, high-intensity activities such as weightlifting, sprinting, or explosive changes of movement (Wyss and Kaddurah-Daouk, 2000; Wallimann et al., 2011; Kreider et al., 2017). Creatine and phosphocreatine also function as spatial and temporal buffers of cellular energy, transporting high-energy phosphate groups between the sites of their production, namely the mitochondria, and the sites of their consumption, such as the myofibrils (Wallimann et al., 2011). Creatine enters muscle cells through a specific sodium- and chloride-dependent creatine transporter (CreaT, SLC6A8). Oral supplementation increases intramuscular concentrations of creatine and phosphocreatine, typically by approximately 15 to 40% (Harris et al., 1992; Hultman et al., 1996; Kreider et al., 2017). However, there is an upper limit to muscle-store saturation that cannot be exceeded indefinitely by further increases in dosage. Individuals with lower baseline concentrations, such as vegetarians, generally show a greater absolute increase, whereas the response is smaller in individuals with high baseline levels. The terms “responder” and “non-responder,” however, are better regarded as a simplified description of a continuum of individual responses rather than a clear division of the population into two groups (Harris et al., 1992; Syrotuik and Bell, 2004; Kreider et al., 2017). After supplementation is discontinued, elevated muscle stores do not immediately return to baseline. They generally decline gradually over several weeks because approximately 1 to 2% of the total pool is converted to creatinine each day. In practical terms, this means that missing a single dose has no measurable acute effect and that creatine works through the long-term elevation and maintenance of muscle stores rather than through a short-term stimulating effect immediately before exercise (Hultman et al., 1996; Kreider et al., 2017). In addition to the classic phosphagen system, other cellular mechanisms have also been described. In cell models, creatine shows direct and indirect antioxidant effects and may protect against oxidative damage by scavenging certain reactive oxygen and nitrogen species, maintaining cellular energy balance, and protecting mitochondrial function. However, the significance of these mechanisms in humans in vivo has not yet been defined as precisely as its role in the ATP-PCr system (Sestili et al., 2011). Taking creatine together with carbohydrates also increases muscle glycogen supercompensation during the first 24 hours of recovery after exhaustive exercise, which may contribute to better recovery between training sessions (Roberts et al., 2016). The ergogenic effects of creatine on strength, performance, and body composition are among the best-documented effects of any dietary supplement. Meta-analyses consistently show benefits, particularly when creatine is combined with resistance training. A large meta-analysis of one hundred studies demonstrated small but statistically significant effect sizes for both body composition and phosphagen-system tasks lasting up to thirty seconds, with the largest effect observed in upper-body exercises (Branch, 2003). Subsequent systematic reviews with meta-analysis separately confirmed significant improvements in lower-extremity muscle strength (Lanhers et al., 2015) and upper-extremity muscle strength (Lanhers et al., 2017). Supplementation increases gains in fat-free mass, although part of the initial weight gain, typically around one to two kilograms in the first few weeks, is attributed to increased intracellular water retention resulting from the osmotic effect of creatine (Kreider et al., 2017). More recent quantitative syntheses have refined this conclusion. A meta-analysis of twelve studies in adults under 50 years of age showed that adding creatine to resistance training increased fat-free mass by an average of 1.14 kg more than training alone and also resulted in a small reduction in body-fat percentage and fat mass (Desai et al., 2024). Another meta-analysis of 23 studies reported an average additional strength gain of approximately 4.43 kg in upper-body exercises and 11.35 kg in lower-body exercises when creatine was combined with resistance training, although the absolute effect size varied depending on the test used, training status, sex, and intervention duration (Wang et al., 2024). In contrast, a meta-analysis of direct imaging measurements of muscle hypertrophy using magnetic resonance imaging, computed tomography, and ultrasound showed only a small additional effect of creatine beyond resistance training alone, with a pooled effect size of approximately 0.11. The result supports the existence of a small direct benefit for regional muscle hypertrophy but does not determine what proportion of the early increase in total fat-free mass is due to intracellular water and what proportion is due to newly formed muscle tissue (Burke et al., 2023). The mechanisms through which creatine may contribute to hypertrophy in addition to water retention remain under investigation and involve several pathways. Besides enabling greater training volume and intensity, and therefore a stronger training stimulus, a direct effect on myogenic processes has also been proposed. During resistance training, creatine may increase the number of satellite cells and myonuclei, promote the expression of myogenic regulatory factors and insulin-like growth factor 1 (IGF-1), and reduce serum concentrations of myostatin, a negative regulator of muscle growth (Louis et al., 2004; Olsen et al., 2006; Saremi et al., 2010). Some of these mechanisms are supported by cell models or smaller and shorter intervention studies, and their relative importance for long-term hypertrophy in humans remains the subject of further research. In addition to skeletal muscle, creatine is also important for energy supply in the brain because the brain is a metabolically demanding organ and can also synthesize creatine locally. However, the cognitive and neurological effects are less firmly established than the effects on physical performance (Braissant and Henry, 2008; Kreider and Stout, 2021). A double-blind, placebo-controlled study showed a beneficial effect of supplementation on working memory and intelligence-test performance. However, it is important to emphasize that the participants were vegetarians, in whom a greater potential for increasing creatine stores would be expected (Rae et al., 2003). Another study reported a beneficial effect on mood as well as cognitive and psychomotor tasks following sleep deprivation combined with mild physical exertion (McMorris et al., 2006). A systematic review of randomized studies concluded that creatine may improve short-term memory and reasoning in healthy individuals, whereas results in other cognitive domains are inconsistent and often remain unchanged in younger individuals under normal conditions (Avgerinos et al., 2018). A benefit therefore appears more likely in individuals with lower baseline stores, older adults, or under conditions of increased metabolic demand. A meta-analysis of sixteen randomized studies involving 492 adults reported small beneficial effects on memory, the time required for attention tasks, and information-processing speed, but no convincing effect on global cognitive performance or executive functions. The certainty of evidence was rated as moderate only for memory (Xu et al., 2024). These results must, however, be interpreted cautiously because a subsequent methodological analysis pointed out that several correlated outcomes from the same participants had been counted as independent observations in the meta-analysis. This could have artificially increased the precision of the pooled estimates and increased the risk of false-positive conclusions (Citherlet, 2026). A similar issue affected a meta-analysis on memory that had originally reported a small beneficial effect of creatine, stronger in older adults than in younger adults (Prokopidis et al., 2023a). After concerns were raised about double-counting dependent outcomes and a subsequent recalculation was performed, the overall effect on memory was no longer statistically significant, whereas the favorable result in the subgroup of older adults remained (Eckert and Pascher, 2023; Prokopidis et al., 2023b; Citherlet, 2026). Particularly interesting findings have been observed under conditions of metabolic stress. A single high dose of creatine at 0.35 g/kg partially reversed the decline in cognitive performance and changes in cerebral high-energy phosphates during sleep deprivation (Gordji-Nejad et al., 2024). A subsequent study showed attenuation of performance decline even after a lower single dose of 0.20 g/kg, although the effect was less pronounced than with the higher dose (Gordji-Nejad et al., 2026). Overall, these data support the possibility of a targeted benefit under certain stress conditions, but not the claim that creatine functions as a universal nootropic. Among other areas investigated, such as recovery, reduction of fatigue, and especially the health of aging individuals, the combination of creatine with resistance training in older adults is the best supported. A meta-analysis of randomized studies showed that adding creatine to resistance training in older individuals resulted in an additional increase in lean tissue mass of approximately 1.4 kg and greater improvements in muscle strength compared with training alone, making creatine a promising supportive intervention against sarcopenia (Chilibeck et al., 2017). In older adults, the combination with regular physical activity is particularly important. A meta-analysis of 20 studies involving 1,093 older individuals showed a small but statistically significant additional improvement in maximal strength when creatine was combined with exercise, whereas the effect on whole-body bone mineral density was not significant (Sharifian et al., 2025). In postmenopausal women, a more recent synthesis of seven randomized studies found an average additional increase in lean mass of 0.37 kg and an improvement in leg-press 1RM of 7.5 kg, with benefits particularly apparent at doses of at least 5 g daily in combination with resistance training. The pooled effect on bone mineral density was not significant (Naddafha et al., 2026). Women’s health across the lifespan appears to represent a distinct area of research, because hormonal changes during the menstrual cycle, pregnancy, and menopause may influence creatine metabolism and the response to supplementation (Smith-Ryan et al., 2021; Smith-Ryan et al., 2025). Clinical data for pregnancy and perimenopause are still limited, however, and much of the rationale is based on mechanistic or preclinical findings, so firm recommendations cannot be made. Outside the musculoskeletal system, creatine is also being investigated in mental health and bone health, although the findings must be presented cautiously. As an adjunctive intervention for depression, creatine produced an average reduction in depressive symptoms and a higher likelihood of remission in one meta-analysis. However, the clinical relevance of this finding remains unclear because of the small number of studies, heterogeneity of interventions, and low to very low certainty of part of the evidence (Eckert et al., 2025). Findings in bone health are conflicting. A twelve-month study in postmenopausal women reported less loss of femoral-neck bone mineral density and favorable changes in certain parameters of bone geometry when creatine was combined with resistance training (Chilibeck et al., 2015). In contrast, a two-year study was unable to demonstrate an increase in bone mineral density, although creatine favorably influenced several geometric parameters of the proximal femur related to bone strength (Chilibeck et al., 2023). Another two-year study using a dose of 3 g daily without concurrent structured resistance training found no improvement in bone health (Sales et al., 2020). A possible benefit of creatine in traumatic brain injury has also been investigated preliminarily. An open-label pilot study involving 39 children and adolescents reported improvements in several clinical outcomes and post-traumatic symptoms after administration of 0.4 g/kg daily for six months (Sakellaris et al., 2006). Because of the small sample size, open-label design, pediatric population, and lack of blinding, however, these results cannot be considered evidence of clinical efficacy. These research areas are promising but currently do not support strong clinical claims.
Two main dosing protocols are used to saturate muscle creatine stores. The classic protocol with a loading phase consists of taking approximately 20 g daily, divided into four doses of 5 g each, for five to seven days. Such a regimen increases muscle creatine content by approximately 20%, after which this level is maintained with a lower dose (Hultman et al., 1996; Kreider et al., 2017). In practice, 3 to 5 g daily is commonly recommended for maintenance. The alternative protocol without a loading phase uses a lower dose of approximately 3 g daily from the outset for about four weeks, achieving the same level of saturation, only more slowly (Hultman et al., 1996; Buford et al., 2007; Kreider et al., 2017). Regarding timing, combining creatine with carbohydrates, and optionally with protein, improves retention and uptake into muscle tissue through an insulin-mediated response (Green et al., 1996; Steenge et al., 2000). In the long term, however, consistent daily intake is the main factor, whereas cycling or taking breaks is unnecessary (Kreider et al., 2017; Antonio et al., 2021). The dose can also be expressed relative to body weight. For rapid loading, studies frequently use approximately 0.3 g/kg/day for 5 to 7 days, followed by 0.03 g/kg/day. For most adults, however, a fixed maintenance dose of 3 to 5 g daily is sufficient in practice, while individuals with higher body weight and a large proportion of muscle mass may require the upper end of this range (Kreider et al., 2017). Dividing the loading dose into at least four portions reduces the likelihood of diarrhea and abdominal discomfort, and during long-term use neither precise timing nor cycling or “washout phases” are required (Ostojic and Ahmetovic, 2008; Antonio et al., 2021). Co-ingestion with carbohydrates or a carbohydrate-protein mixture may increase creatine retention, but this requires a relatively strong insulin response and is not necessary for effectiveness in the average user (Green et al., 1996; Steenge et al., 2000). In practical terms, taking creatine with a meal or after training is useful mainly because it makes it easier to establish a regular habit and may improve gastrointestinal tolerance in some individuals. Acute caffeine intake after prior saturation of muscle creatine stores probably does not impair the effects of creatine. However, studies on long-term concurrent use of creatine and caffeine have produced mixed results. Some have reported attenuation of the ergogenic effect, while others have found no negative interaction or even a synergistic effect. In sensitive individuals, taking both at the same time may worsen gastrointestinal discomfort. The available evidence therefore does not support the need to routinely separate creatine and caffeine in time, although doing so may be reasonable if symptoms occur (Trexler et al., 2016; Elosegui et al., 2022). The safety profile of creatine monohydrate is extensively documented and is among the best studied of all dietary supplements, including during long-term use by healthy individuals. Studies of athletes using creatine long term found no adverse effects on kidney function (Poortmans and Francaux, 1999). The widespread myth of kidney damage is based in part on confusion between a biomarker and actual injury, because creatine is converted into creatinine, which is commonly used as an indirect marker of kidney function. A slight increase in serum concentration during supplementation may therefore reflect increased creatinine production and reduce the accuracy of creatinine-based estimates of filtration without necessarily indicating a real decline in renal filtration capacity (Kreider et al., 2017; Antonio et al., 2021; Tsiaras et al., 2026). Nevertheless, caution is warranted in individuals with pre-existing kidney disease, for whom substantially less data are available, and medical consultation is advisable. Actual side effects are generally mild and temporary and include water retention with associated weight gain at the beginning of supplementation, as well as gastrointestinal discomfort with high single doses. These can be reduced by dividing the dose and taking it with food. Claims that creatine causes dehydration and muscle cramps are not supported by scientific evidence (Lopez et al., 2009; Kreider et al., 2017). The most recent meta-analysis of randomized trials showed a small increase in serum creatinine of approximately 0.13 mg/dl, but no significant change in urea or estimated glomerular filtration rate. This supports the interpretation that creatinine becomes a less specific marker of kidney function during supplementation (Tsiaras et al., 2026). In cases of clinical uncertainty, cystatin C or directly measured glomerular filtration rate may be considered alongside medical history, urinalysis, and standard laboratory parameters (Neves et al., 2011; Tsiaras et al., 2026). Safety conclusions apply primarily to healthy individuals and usual dosages. In the presence of known kidney disease, nephrotoxic medication, pregnancy, or breastfeeding, individualized medical assessment is appropriate because less clinical evidence is available for these groups (Antonio et al., 2021; Smith-Ryan et al., 2021; Tsiaras et al., 2026). Another frequently repeated myth is the claim that creatine causes hair loss. This is based on a single study in which dihydrotestosterone levels and the ratio of dihydrotestosterone to testosterone increased after a loading phase, although neither hair loss nor the condition of hair follicles was measured at all (van der Merwe et al., 2009). This hormonal finding has not been convincingly replicated. A review of twelve studies found no consistent effect of creatine on testosterone or dihydrotestosterone (Antonio et al., 2021), and a randomized study from 2025 that directly examined hair density, hair-shaft thickness, and the condition of hair follicles found no difference compared with placebo (Lak et al., 2025). Claims concerning dehydration and muscle cramps have also been refuted by a systematic review with meta-analysis, according to which creatine does not impair fluid balance, thermoregulation, or the ability to dissipate heat during exercise in warm environments (Lopez et al., 2009). From a regulatory perspective, creatine monohydrate is commonly marketed in the European Union, and therefore also in the Czech Republic, as an ingredient in dietary supplements. Products are subject to general food law, legislation governing food supplements, and rules concerning nutrition and health claims (European Parliament and Council, 2002; European Commission, 2012). Based on positive scientific assessments by EFSA, the European Commission has authorized two health claims for creatine. In 2011, EFSA issued a positive assessment of the claim that creatine increases physical performance in successive bursts of short-term, high-intensity exercise. The claim was subsequently added to the Union list of permitted claims with the condition of a daily intake of 3 g of creatine (EFSA NDA Panel, 2011a; European Commission, 2012). In 2016, EFSA also positively assessed the claim that daily creatine intake may enhance the effect of resistance training on muscle strength in adults over 55 years of age. The European Commission authorized this claim in 2017. It may be used with a daily intake of 3 g of creatine in conjunction with regular resistance training performed at least three times per week over several weeks (EFSA NDA Panel, 2016; European Commission, 2017). Other proposed claims, for example regarding increased attention or improved memory, were assessed as insufficiently substantiated (EFSA NDA Panel, 2011b). In 2024, EFSA additionally concluded that the submitted evidence did not establish a cause-and-effect relationship between creatine supplementation and improvement in cognitive function. The European Commission therefore refused authorization of this claim in May 2026 (EFSA NDA Panel, 2024; European Commission, 2026). Such claims therefore cannot be used in commercial communications for foods and dietary supplements in the EU. Creatine is also not included on the current World Anti-Doping Agency list of prohibited substances and methods for 2026 and is therefore permitted from an anti-doping perspective. Athletes should nevertheless choose independently tested products because any potential risk may arise from contamination of the dietary supplement with other prohibited substances rather than from creatine itself (WADA, 2025).
Numerous alternative chemical forms of creatine are available on the market and are often promoted as more effective, more soluble, or more stable than monohydrate. Among the best known are creatine hydrochloride, creatine ethyl ester, buffered creatine (Kre-Alkalyn), creatine malate, and creatine nitrate. Critical reviews, however, repeatedly conclude that the efficacy, safety, and regulatory status of most of these newer forms are insufficiently established and that there is no convincing evidence that they are more stable, absorbed more rapidly, more effective at increasing muscle creatine, or associated with fewer side effects than monohydrate (Jäger et al., 2011; Fazio et al., 2022; Kreider et al., 2022). An analysis of commercially available alternative creatine forms also found that most claims of superiority have little or no direct scientific basis (Escalante et al., 2022). Many of these forms additionally contain less pure creatine per gram of the finished compound and are more expensive, so creatine monohydrate remains the gold standard with the best balance of cost, effectiveness, and scientific evidence (Escalante et al., 2022; Kreider et al., 2022). Comparison of different forms should be based on whether the respective product demonstrably increases total and phosphorylated creatine content in muscle, whether it improves performance compared with an equimolar dose of monohydrate, and whether its safety is well characterized (Jäger et al., 2011; Kreider et al., 2022). In the case of creatine ethyl ester, a randomized controlled trial showed a lower ability to increase serum and muscle creatine concentrations and, conversely, greater creatinine formation compared with monohydrate (Spillane et al., 2009), while the buffered form Kre-Alkalyn produced no greater changes in muscle creatine, body composition, or training adaptation than monohydrate in a double-blind study (Jagim et al., 2012). For hydrochloride, malate, citrate, nitrate, and other mixtures, convincing evidence of any practically relevant superiority over an equivalent dose of creatine monohydrate is lacking. A possible advantage may lie in taste, solubility, dosage form, or individual tolerance, but not in a demonstrably greater ability to increase muscle creatine stores or in superior ergogenic effectiveness (Jäger et al., 2011; Fazio et al., 2022; Kreider et al., 2022). Greater solubility in water by itself does not demonstrate better bioavailability or greater storage of creatine in muscle tissue. In addition to different forms of creatine, several other ergogenic dietary supplements are available with differing mechanisms and levels of evidence.
Beta-alanine is the rate-limiting precursor of carnosine synthesis, an intracellular pH buffer in muscle. Supplementation with 4 to 6 g daily for at least two to four weeks increases muscle carnosine levels and may improve performance particularly during intense exercise lasting approximately one to four minutes (Trexler et al., 2015; Saunders et al., 2017).
Beta-hydroxy-beta-methylbutyrate (HMB), a metabolite of leucine, may under certain conditions reduce markers of exercise-induced muscle damage and support recovery, although study findings are inconsistent (Wilson et al., 2013). A meta-analysis focusing on younger individuals likewise found no significant additional benefit of HMB for changes in body composition or muscle strength during resistance training (Jakubowski et al., 2020).
Whey protein and other high-quality proteins provide essential amino acids, including leucine, which are required to stimulate muscle protein synthesis. Their benefit for increasing muscle mass and strength during resistance training is well established, particularly when they help achieve an adequate total daily protein intake (Jäger et al., 2017; Morton et al., 2018).
Caffeine is a well-established ergogenic stimulant that can improve aerobic endurance, muscular endurance, and certain forms of anaerobic performance, increase alertness, and reduce perceived exertion. However, its effects vary between individuals and depend on the dose, type of exercise, habituation to caffeine, and genetic and other individual characteristics (Guest et al., 2021).
Citrulline malate is promoted for supporting arginine availability and nitric oxide production and may slightly increase the number of repetitions performed to muscular failure during resistance exercise, although the effect size is small. A meta-analysis found an average of approximately three additional repetitions after acute intake of 6 to 8 g of citrulline malate, although the finding was not equally convincing for all muscle groups and training modalities (Vårvik et al., 2021).
Betaine, or trimethylglycine, acts as an osmolyte and methyl-group donor, but its effects on athletic performance remain unclear. A more recent meta-analysis suggested a moderate benefit for maximal strength, particularly in the lower extremities, but not a consistent effect on muscular endurance, sprint performance, or other investigated outcomes (Zawieja et al., 2024).
Despite these alternatives and complementary supplements, creatine monohydrate remains one of the dietary supplements with the strongest and most consistent scientific evidence for increasing repeated high-intensity exercise capacity, muscle strength, and gains in fat-free mass during resistance training (Kreider et al., 2017).
Among other ergogenic substances for which the International Society of Sports Nutrition has issued a position stand, sodium bicarbonate may be mentioned. At a dose of approximately 0.2 to 0.5 g/kg, it may improve high-intensity performance during exercise lasting roughly 30 seconds to 12 minutes. Its combination with creatine or beta-alanine may under certain conditions provide an additive effect, although the available findings are not consistent enough to guarantee such a benefit for every type of exercise and dosing protocol (Grgic et al., 2021).
From a practical perspective, these substances do not completely overlap but rather complement one another depending on the type of performance. Creatine is best suited to repeated short, intense efforts and to supporting adaptations to resistance training; beta-alanine particularly to intense efforts lasting approximately one to four minutes; caffeine to acutely increasing alertness, reducing perceived exertion, and supporting various forms of performance; and protein to ensuring an adequate daily intake of essential amino acids. A combination product is useful only when each individual component matches the user’s goal and is present at an effective dose. In terms of the balance between cost and evidence, pure creatine monohydrate remains the first choice among the various forms of creatine (Escalante et al., 2022; Fazio et al., 2022; Kreider et al., 2022).
Written for Kratom World by:
Ing. Matěj Malík, Ph.D.
Research Fellow, Postdoctoral Researcher
Faculty of Agrobiology, Food and Natural Resources, Czech University of Life Sciences Prague
Department of Agroenvironmental Chemistry and Plant Nutrition

References
Albagachiev, S.A., Pinegina, E.D., Sadkovskii, I.A., Krasnyuk, I.I., Mandrik, M.A., 2026. State of the Art and Development Trends in Obtaining Fast-Dissolving Forms of Creatine Monohydrate. Pharmaceuticals. 19, 128. https://doi.org/10.3390/ph19010128
Antonio, J., Candow, D.G., Forbes, S.C., Gualano, B., Jagim, A.R., Kreider, R.B., Rawson, E.S., Smith-Ryan, A.E., VanDusseldorp, T.A., Willoughby, D.S., Ziegenfuss, T.N., 2021. Common questions and misconceptions about creatine supplementation: what does the scientific evidence really show? Journal of the International Society of Sports Nutrition. 18, 13. https://doi.org/10.1186/s12970-021-00412-w
Avgerinos, K.I., Spyrou, N., Bougioukas, K.I., Kapogiannis, D., 2018. Effects of creatine supplementation on cognitive function of healthy individuals: A systematic review of randomized controlled trials. Experimental Gerontology. 108, 166-173. https://doi.org/10.1016/j.exger.2018.04.013
Benzi, G., 2000. Is there a rationale for the use of creatine either as nutritional supplementation or drug administration in humans participating in a sport? Pharmacological Research. 41, 255–264. https://doi.org/10.1006/phrs.1999.0618
Bonilla, D.A., Kreider, R.B., Stout, J.R., Forero, D.A., Kerksick, C.M., Roberts, M.D., Rawson, E.S., 2021. Metabolic Basis of Creatine in Health and Disease: A Bioinformatics-Assisted Review. Nutrients. 13, 1238. https://doi.org/10.3390/nu13041238
Braissant, O., Henry, H., 2008. AGAT, GAMT and SLC6A8 distribution in the central nervous system, in relation to creatine deficiency syndromes: a review. Journal of Inherited Metabolic Disease. 31, 230-239. https://doi.org/10.1007/s10545-008-0826-9
Branch, J.D., 2003. Effect of creatine supplementation on body composition and performance: a meta-analysis. International Journal of Sport Nutrition and Exercise Metabolism. 13, 198-226. https://doi.org/10.1123/ijsnem.13.2.198
Bredahl, E.C., Eckerson, J.M., Tracy, S.M., McDonald, T.L., Drescher, K.M., 2021. The role of creatine in the development and activation of immune responses. Nutrients. 13, 751. https://doi.org/10.3390/nu13030751
Brosnan, J.T., Brosnan, M.E., 2007. Creatine: endogenous metabolite, dietary, and therapeutic supplement. Annual Review of Nutrition. 27, 241-261. https://doi.org/10.1146/annurev.nutr.27.061406.093621
Buford, T.W., Kreider, R.B., Stout, J.R., Greenwood, M., Campbell, B., Spano, M., Ziegenfuss, T., Lopez, H., Landis, J., Antonio, J., 2007. International Society of Sports Nutrition position stand: creatine supplementation and exercise. Journal of the International Society of Sports Nutrition. 4, 6. https://doi.org/10.1186/1550-2783-4-6
Burke, D.G., Chilibeck, P.D., Parise, G., Candow, D.G., Mahoney, D., Tarnopolsky, M., 2003. Effect of creatine and weight training on muscle creatine and performance in vegetarians. Medicine & Science in Sports & Exercise. 35, 1946-1955. https://doi.org/10.1249/01.MSS.0000093614.17517.79
Burke, R., Piñero, A., Coleman, M., Mohan, A., Sapuppo, M., Augustin, F., Aragon, A.A., Candow, D.G., Forbes, S.C., Swinton, P., Schoenfeld, B.J., 2023. The Effects of Creatine Supplementation Combined with Resistance Training on Regional Measures of Muscle Hypertrophy: A Systematic Review with Meta-Analysis. Nutrients. 15, 2116. https://doi.org/10.3390/nu15092116
Chilibeck, P.D., Candow, D.G., Gordon, J.J., Duff, W.R.D., Mason, R., Shaw, K., Taylor-Gjevre, R., Nair, B., Zello, G.A., 2023. A 2-yr Randomized Controlled Trial on Creatine Supplementation during Exercise for Postmenopausal Bone Health. Medicine & Science in Sports & Exercise. 55, 1750–1760. https://doi.org/10.1249/MSS.0000000000003202
Chilibeck, P.D., Candow, D.G., Landeryou, T., Kaviani, M., Paus-Jenssen, L., 2015. Effects of Creatine and Resistance Training on Bone Health in Postmenopausal Women. Medicine & Science in Sports & Exercise. 47, 1587–1595. https://doi.org/10.1249/MSS.0000000000000571
Chilibeck, P.D., Kaviani, M., Candow, D.G., Zello, G.A., 2017. Effect of creatine supplementation during resistance training on lean tissue mass and muscular strength in older adults: a meta-analysis. Open Access Journal of Sports Medicine. 8, 213–226. https://doi.org/10.2147/OAJSM.S123529
Citherlet, T., 2026. Commentary: The effects of creatine supplementation on cognitive function in adults: a systematic review and meta-analysis. Frontiers in Nutrition. 13, 1716285. https://doi.org/10.3389/fnut.2026.1716285
Dash, A.K., Mo, Y., Pyne, A., 2002. Solid-state properties of creatine monohydrate. Journal of Pharmaceutical Sciences. 91, 708–718. https://doi.org/10.1002/jps.10073
Desai, I., Wewege, M.A., Jones, M.D., Clifford, B.K., Pandit, A., Kaakoush, N.O., Simar, D., Hagstrom, A.D., 2024. The Effect of Creatine Supplementation on Resistance Training-Based Changes to Body Composition: A Systematic Review and Meta-analysis. Journal of Strength and Conditioning Research. 38, 1813-1821. https://doi.org/10.1519/JSC.0000000000004862
Eckert, I., Lima, J., Dariva, A.A., 2025. Creatine supplementation for treating symptoms of depression: a systematic review and meta-analysis. British Journal of Nutrition. 134, 947-959. https://doi.org/10.1017/S0007114525105588
Eckert, I., Pascher, E., 2023. Letter to the Editor: Double-counting due to inadequate statistics leads to false-positive findings in “Effects of creatine supplementation on memory in healthy individuals: a systematic review and meta-analysis of randomized controlled trials.” Nutrition Reviews. 81, 1495–1496. https://doi.org/10.1093/nutrit/nuac108
EFSA NDA Panel, 2011a. Scientific Opinion on the substantiation of health claims related to creatine and increase in physical performance during short-term, high intensity, repeated exercise bouts and increase in endurance capacity pursuant to Article 13(1) of Regulation (EC) No 1924/2006. EFSA Journal. 9, 2303. https://doi.org/10.2903/j.efsa.2011.2303
EFSA NDA Panel, 2011b. Scientific Opinion on the substantiation of health claims related to creatine and increased attention and improvement of memory pursuant to Article 13(1) of Regulation (EC) No 1924/2006. EFSA Journal. 9, 2216. https://doi.org/10.2903/j.efsa.2011.2216
EFSA NDA Panel, 2016. Creatine in combination with resistance training and improvement in muscle strength: evaluation of a health claim pursuant to Article 13(5) of Regulation (EC) No 1924/2006. EFSA Journal. 14, 4400. https://doi.org/10.2903/j.efsa.2016.4400
EFSA NDA Panel, 2024. Creatine and improvement in cognitive function: evaluation of a health claim pursuant to Article 13(5) of Regulation (EC) No 1924/2006. EFSA Journal. 22, e9100. https://doi.org/10.2903/j.efsa.2024.9100
Elosegui, S., López-Seoane, J., Martínez-Ferrán, M., Pareja-Galeano, H., 2022. Interaction between caffeine and creatine when used as concurrent ergogenic supplements: a systematic review. International Journal of Sport Nutrition and Exercise Metabolism. 32, 285–295. https://doi.org/10.1123/ijsnem.2021-0262
Escalante, G., Gonzalez, A.M., St Mart, D., Torres, M., Echols, J., Islas, M., Schoenfeld, B.J., 2022. Analysis of the efficacy, safety, and cost of alternative forms of creatine available for purchase on Amazon.com: Are label claims supported by science? Heliyon. 8, e12113. https://doi.org/10.1016/j.heliyon.2022.e12113
European Commission, 2012. Commission Regulation (EU) No 432/2012 of 16 May 2012 establishing a list of permitted health claims made on foods, other than those referring to the reduction of disease risk and to children’s development and health. Official Journal of the European Union. L 136, 1–40. https://eur-lex.europa.eu/eli/reg/2012/432/oj
European Commission, 2017. Commission Implementing Regulation (EU) 2017/672 of 7 April 2017 authorising a health claim made on foods and amending Regulation (EU) No 432/2012. Official Journal of the European Union. L 97, 24–26. https://eur-lex.europa.eu/eli/reg_impl/2017/672/oj
European Commission, 2026. Commission Regulation (EU) 2026/1118 of 26 May 2026 refusing to authorise a health claim made on foods, other than those referring to the reduction of disease risk and to children’s development and health. Official Journal of the European Union. https://eur-lex.europa.eu/eli/reg/2026/1118/oj
European Parliament and Council, 2002. Directive 2002/46/EC of 10 June 2002 on the approximation of the laws of the Member States relating to food supplements. Official Journal of the European Communities. L 183, 51–57. https://eur-lex.europa.eu/eli/dir/2002/46/oj
Fazio, C., Elder, C.L., Harris, M.M., 2022. Efficacy of Alternative Forms of Creatine Supplementation on Improving Performance and Body Composition in Healthy Subjects: A Systematic Review. Journal of Strength and Conditioning Research. 36, 2663–2670. https://doi.org/10.1519/JSC.0000000000003873
Ganguly, S., Jayappa, S., Dash, A.K., 2003. Evaluation of the stability of creatine in solution prepared from effervescent creatine formulations. AAPS PharmSciTech. 4, 119–128. https://doi.org/10.1208/pt040225
Gordji-Nejad, A., Matusch, A., Hengstler, L., Beer, S., Kroll, T., Klein, S., Elmenhorst, D., Bauer, A., Drzezga, A., 2026. Single-Dose Creatine Reduces Sleep Deprivation-Induced Deterioration in Cognitive Performance. Nutrients. 18, 1192. https://doi.org/10.3390/nu18081192
Gordji-Nejad, A., Matusch, A., Kleedörfer, S., Patel, H.J., Drzezga, A., Elmenhorst, D., Binkofski, F., Bauer, A., 2024. Single dose creatine improves cognitive performance and induces changes in cerebral high energy phosphates during sleep deprivation. Scientific Reports. 14, 4937. https://doi.org/10.1038/s41598-024-54249-9
Green, A.L., Hultman, E., Macdonald, I.A., Sewell, D.A., Greenhaff, P.L., 1996. Carbohydrate ingestion augments skeletal muscle creatine accumulation during creatine supplementation in humans. American Journal of Physiology. 271, E821-E826. https://doi.org/10.1152/ajpendo.1996.271.5.E821
Grgic, J., Pedisic, Z., Saunders, B., Artioli, G.G., Schoenfeld, B.J., McKenna, M.J., Bishop, D.J., Kreider, R.B., Stout, J.R., Kalman, D.S., Arent, S.M., VanDusseldorp, T.A., Lopez, H.L., Ziegenfuss, T.N., Burke, L.M., Antonio, J., Campbell, B.I., 2021. International Society of Sports Nutrition position stand: sodium bicarbonate and exercise performance. Journal of the International Society of Sports Nutrition. 18, 61. https://doi.org/10.1186/s12970-021-00458-w
Guest, N.S., VanDusseldorp, T.A., Nelson, M.T., Grgic, J., Schoenfeld, B.J., Jenkins, N.D.M., Arent, S.M., Antonio, J., Stout, J.R., Trexler, E.T., Smith-Ryan, A.E., Goldstein, E.R., Kalman, D.S., Campbell, B.I., 2021. International society of sports nutrition position stand: caffeine and exercise performance. Journal of the International Society of Sports Nutrition. 18, 1. https://doi.org/10.1186/s12970-020-00383-4
Harris, R.C., Söderlund, K., Hultman, E., 1992. Elevation of creatine in resting and exercised muscle of normal subjects by creatine supplementation. Clinical Science. 83, 367-374. https://doi.org/10.1042/cs0830367
Hultman, E., Söderlund, K., Timmons, J.A., Cederblad, G., Greenhaff, P.L., 1996. Muscle creatine loading in men. Journal of Applied Physiology. 81, 232-237. https://doi.org/10.1152/jappl.1996.81.1.232
Jäger, R., Kerksick, C.M., Campbell, B.I., Cribb, P.J., Wells, S.D., Skwiat, T.M., Purpura, M., Ziegenfuss, T.N., Ferrando, A.A., Arent, S.M., Smith-Ryan, A.E., Stout, J.R., Arciero, P.J., Ormsbee, M.J., Taylor, L.W., Wilborn, C.D., Kalman, D.S., Kreider, R.B., Willoughby, D.S., Hoffman, J.R., Krzykowski, J.L., Antonio, J., 2017. International Society of Sports Nutrition Position Stand: protein and exercise. Journal of the International Society of Sports Nutrition. 14, 20. https://doi.org/10.1186/s12970-017-0177-8
Jäger, R., Purpura, M., Shao, A., Inoue, T., Kreider, R.B., 2011. Analysis of the efficacy, safety, and regulatory status of novel forms of creatine. Amino Acids. 40, 1369–1383. https://doi.org/10.1007/s00726-011-0874-6
Jagim, A.R., Oliver, J.M., Sanchez, A., Galvan, E., Fluckey, J., Riechman, S., Greenwood, M., Kelly, K., Meininger, C., Rasmussen, C., Kreider, R.B., 2012. A buffered form of creatine does not promote greater changes in muscle creatine content, body composition, or training adaptations than creatine monohydrate. Journal of the International Society of Sports Nutrition. 9, 43. https://doi.org/10.1186/1550-2783-9-43
Jakubowski, J.S., Wong, E.P.T., Nunes, E.A., Noguchi, K.S., Vandeweerd, J.K., Murphy, K.T., Morton, R.W., McGlory, C., Phillips, S.M., 2020. Equivalent hypertrophy and strength gains in β-hydroxy-β-methylbutyrate- or leucine-supplemented men. Medicine & Science in Sports & Exercise. 52, 1575–1585.
Kaviani, M., Shaw, K., Chilibeck, P.D., 2020. Benefits of creatine supplementation for vegetarians compared to omnivorous athletes: A systematic review. International Journal of Environmental Research and Public Health. 17, 3041. https://doi.org/10.3390/ijerph17093041
Kreider, R.B., Kalman, D.S., Antonio, J., Ziegenfuss, T.N., Wildman, R., Collins, R., Candow, D.G., Kleiner, S.M., Almada, A.L., Lopez, H.L., 2017. International Society of Sports Nutrition position stand: safety and efficacy of creatine supplementation in exercise, sport, and medicine. Journal of the International Society of Sports Nutrition. 14, 18. https://doi.org/10.1186/s12970-017-0173-z
Kreider, R.B., Stout, J.R., 2021. Creatine in Health and Disease. Nutrients. 13, 447. https://doi.org/10.3390/nu13020447
Kreider, R.B., Stout, J.R., Candow, D.G., 2022. The creatine monohydrate saga: challenges and opportunities for future research. Journal of the International Society of Sports Nutrition. 19, 1–18.
Lak, M., Forbes, S.C., Candow, D.G., et al., 2025. Creatine supplementation does not affect hair density, follicular unit count, or hair thickness: a randomized controlled trial. Journal of the International Society of Sports Nutrition.
Lanhers, C., Pereira, B., Naughton, G., Trousselard, M., Lesage, F.X., Dutheil, F., 2015. Creatine supplementation and lower limb strength performance: a systematic review and meta-analysis. Sports Medicine. 45, 1285–1294.
Lanhers, C., Pereira, B., Naughton, G., Trousselard, M., Lesage, F.X., Dutheil, F., 2017. Creatine supplementation and upper limb strength performance: a systematic review and meta-analysis. Sports Medicine. 47, 163–173.
Lopez, R.M., Casa, D.J., McDermott, B.P., Ganio, M.S., Armstrong, L.E., Maresh, C.M., 2009. Does creatine supplementation hinder exercise heat tolerance or hydration status? A systematic review with meta-analyses. Journal of Athletic Training. 44, 215–223.
Louis, M., Poortmans, J.R., Francaux, M., Hultman, E., Berre, J., Boisseau, N., Young, V.R., Smith, K., Meier-Augenstein, W., Babraj, J.A., Waddell, T., 2004. No effect of creatine supplementation on human myofibrillar and sarcoplasmic protein synthesis after resistance exercise. American Journal of Physiology-Endocrinology and Metabolism. 285, E1089–E1094.
McMorris, T., Harris, R.C., Swain, J., Corbett, J., Collard, K., Dyson, R.J., Dye, L., Hodgson, C., Draper, N., 2006. Effect of creatine supplementation and sleep deprivation, with mild exercise, on cognitive and psychomotor performance, mood state, and plasma concentrations of catecholamines and cortisol. Psychopharmacology. 185, 93–103.
Moret, S., Prevarin, A., Tubaro, F., 2011. Levels of creatine, organic contaminants and heavy metals in creatine dietary supplements. Food Chemistry. 126, 1232–1238.
Morton, R.W., Murphy, K.T., McKellar, S.R., et al., 2018. A systematic review, meta-analysis and meta-regression of the effect of protein supplementation on resistance training-induced gains in muscle mass and strength in healthy adults. British Journal of Sports Medicine. 52, 376–384.
Naddafha, M., et al., 2026. Creatine supplementation and resistance training in postmenopausal women: systematic review and meta-analysis.
Neves, M., Gualano, B., Roschel, H., et al., 2011. Effect of creatine supplementation on measured glomerular filtration rate in postmenopausal women. Applied Physiology, Nutrition, and Metabolism. 36, 419–422.
Olsen, S., Aagaard, P., Kadi, F., et al., 2006. Creatine supplementation augments the increase in satellite cell and myonuclei number in human skeletal muscle induced by strength training. Journal of Physiology. 573, 525–534.
Ostojic, S.M., Ahmetovic, Z., 2008. Gastrointestinal distress after creatine supplementation in athletes: are side effects dose dependent? Research in Sports Medicine. 16, 15–22.
Persky, A.M., Brazeau, G.A., 2001. Clinical pharmacology of the dietary supplement creatine monohydrate. Pharmacological Reviews. 53, 161–176.
Persky, A.M., Müller, M., Derendorf, H., Grant, M., Brazeau, G.A., Hochhaus, G., 2003. Single- and multiple-dose pharmacokinetics of oral creatine. Journal of Clinical Pharmacology. 43, 29–37.
Poortmans, J.R., Francaux, M., 1999. Long-term oral creatine supplementation does not impair renal function in healthy athletes. Medicine & Science in Sports & Exercise. 31, 1108–1110.
Prokopidis, K., Giannos, P., Triantafyllidis, K.K., et al., 2023a. Effects of creatine supplementation on memory in healthy individuals: a systematic review and meta-analysis of randomized controlled trials. Nutrition Reviews. 81, 416–427.
Prokopidis, K., et al., 2023b. Response to Letter to the Editor regarding double-counting in creatine and memory meta-analysis. Nutrition Reviews.
Rae, C., Digney, A.L., McEwan, S.R., Bates, T.C., 2003. Oral creatine monohydrate supplementation improves brain performance: a double-blind, placebo-controlled, cross-over trial. Proceedings of the Royal Society B: Biological Sciences. 270, 2147–2150.
Roberts, P.A., Fox, J., Peirce, N., Jones, S.W., Casey, A., Greenhaff, P.L., 2016. Creatine ingestion augments dietary carbohydrate mediated muscle glycogen supercompensation during the initial 24 h of recovery following prolonged exhaustive exercise in humans. Amino Acids. 48, 1831–1842.
Roschel, H., Gualano, B., Ostojic, S.M., Rawson, E.S., 2021. Creatine supplementation and brain health. Nutrients. 13, 586.
Sakellaris, G., Kotsiou, M., Tamiolaki, M., et al., 2006. Prevention of complications related to traumatic brain injury in children and adolescents with creatine administration: an open label randomized pilot study. Journal of Trauma. 61, 322–329.
Sales, L.P., Pinto, A.J., Rodrigues, S.F., et al., 2020. Creatine supplementation and bone health in postmenopausal women: a randomized controlled trial. Medicine & Science in Sports & Exercise.
Saremi, A., Gharakhanloo, R., Sharghi, S., Gharaati, M.R., Larijani, B., Omidfar, K., 2010. Effects of oral creatine and resistance training on serum myostatin and GASP-1. Molecular and Cellular Endocrinology. 317, 25–30.
Saunders, B., Elliott-Sale, K., Artioli, G.G., et al., 2017. β-alanine supplementation to improve exercise capacity and performance: a systematic review and meta-analysis. British Journal of Sports Medicine. 51, 658–669.
Sestili, P., Martinelli, C., Bravi, G., et al., 2011. Creatine supplementation affords cytoprotection in oxidatively injured cultured mammalian cells via direct antioxidant activity. Free Radical Biology and Medicine. 40, 837–849.
Sharifian, S., et al., 2025. Effects of creatine supplementation combined with exercise on muscle strength and bone health in older adults: systematic review and meta-analysis.
Smith-Ryan, A.E., Cabre, H.E., Eckerson, J.M., Candow, D.G., 2021. Creatine supplementation in women’s health: a lifespan perspective. Nutrients. 13, 877.
Smith-Ryan, A.E., et al., 2025. Creatine across the female lifespan: emerging evidence and future directions.
Spillane, M., Schoch, R., Cooke, M., et al., 2009. The effects of creatine ethyl ester supplementation combined with heavy resistance training on body composition, muscle performance, and serum and muscle creatine levels. Journal of the International Society of Sports Nutrition. 6, 6.
Steenge, G.R., Simpson, E.J., Greenhaff, P.L., 2000. Protein- and carbohydrate-induced augmentation of whole body creatine retention in humans. Journal of Applied Physiology. 89, 1165–1171.
Syrotuik, D.G., Bell, G.J., 2004. Acute creatine monohydrate supplementation: a descriptive physiological profile of responders vs. nonresponders. Journal of Strength and Conditioning Research. 18, 610–617.
Trexler, E.T., Smith-Ryan, A.E., Stout, J.R., et al., 2015. International Society of Sports Nutrition position stand: Beta-Alanine. Journal of the International Society of Sports Nutrition. 12, 30.
Trexler, E.T., Smith-Ryan, A.E., Roelofs, E.J., Hirsch, K.R., Persky, A.M., Mock, M.G., 2016. Effects of coffee and caffeine anhydrous on strength and sprint performance. European Journal of Sport Science.
Tsiaras, V., et al., 2026. Effects of creatine supplementation on renal function: a systematic review and meta-analysis of randomized controlled trials.
van der Merwe, J., Brooks, N.E., Myburgh, K.H., 2009. Three weeks of creatine monohydrate supplementation affects dihydrotestosterone to testosterone ratio in college-aged rugby players. Clinical Journal of Sport Medicine. 19, 399–404.
Vårvik, F.T., Bjørnsen, T., Gonzalez, A.M., 2021. Acute effect of citrulline malate on repetition performance during strength training: a systematic review and meta-analysis. International Journal of Sport Nutrition and Exercise Metabolism. 31, 350–358.
WADA, 2025. The 2026 Prohibited List. World Anti-Doping Agency.
Wallimann, T., Tokarska-Schlattner, M., Schlattner, U., 2011. The creatine kinase system and pleiotropic effects of creatine. Amino Acids. 40, 1271–1296.
Wang, et al., 2024. Effects of creatine supplementation combined with resistance training on muscular strength: systematic review and meta-analysis.
Wilson, J.M., Fitschen, P.J., Campbell, B., et al., 2013. International Society of Sports Nutrition position stand: beta-hydroxy-beta-methylbutyrate (HMB). Journal of the International Society of Sports Nutrition. 10, 6.
Wyss, M., Kaddurah-Daouk, R., 2000. Creatine and creatinine metabolism. Physiological Reviews. 80, 1107–1213.
Xu, C., et al., 2024. The effects of creatine supplementation on cognitive function in adults: a systematic review and meta-analysis. Frontiers in Nutrition. 11, 1424972. https://doi.org/10.3389/fnut.2024.1424972
Zawieja, E., Machek, S., Zanchi, N.E., Cholewa, J., Woźniewicz, M., 2024. Effects of chronic betaine supplementation on exercise performance: Systematic review and meta-analysis. Journal of Sports Sciences. 42, 2131–2144. https://doi.org/10.1080/02640414.2024.2423578